
 By Alpit Patel and the aibrevo team · September 16, 2026 · Updated October 31, 2026 · 18 min read
GoHighLevel for Dental Practices: No-Show Recovery, Case Acceptance and Recall Automation
How dental practices use GoHighLevel for appointment reminders, no-show recovery, treatment-plan follow-up, hygiene recall and patient reactivation, sized against 2026 Planet DDS and Henry Schein One benchmark data, plus HIPAA/BAA setup.
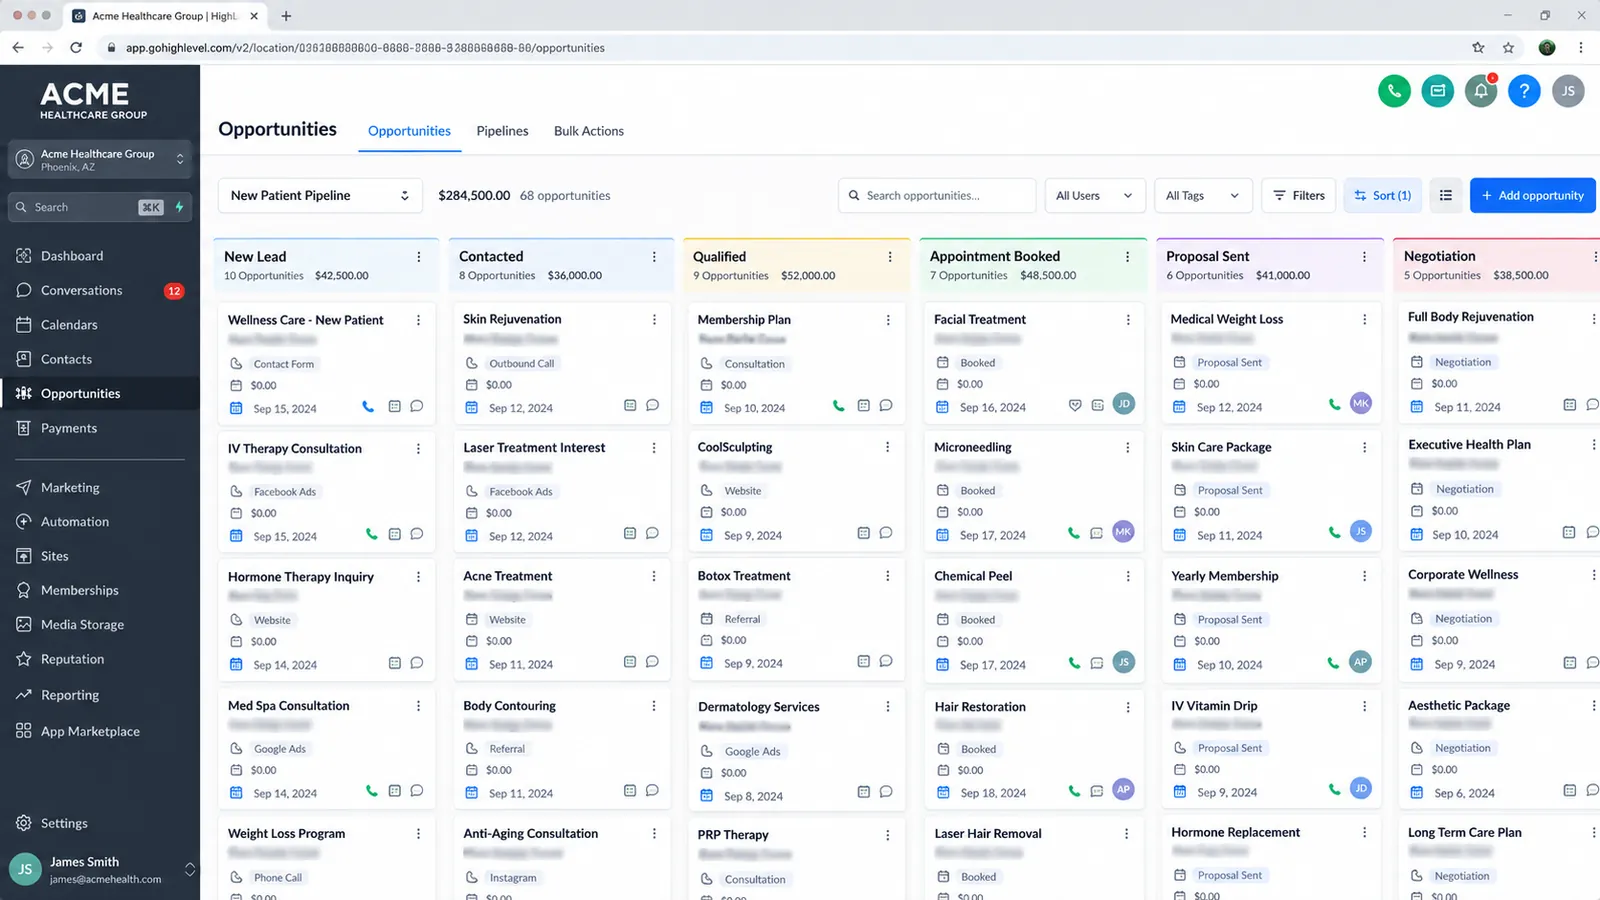
Part of the guide: GoHighLevel by industry
Key takeaways
- Henry Schein One's 2026 Catalyst Index puts case acceptance at 45% for the average practice against 75% for top performers. The report ties the 30-point gap to consistency in how care is diagnosed, presented and accepted, and a treatment-plan follow-up workflow targets the follow-up part of it.
- Planet DDS's March 2026 analysis of 15,000+ practices on Denticon found cancellations down 17% year over year and case completion up from 42% to 47%. Planet DDS ties both shifts to proactive communication and scheduling systems.
- GoHighLevel is not HIPAA compliant by default. Patient information can flow through it only after the agency buys HighLevel's $297/month HIPAA add-on (agency-wide and permanent), signs the Business Associate Agreement, and switches HIPAA on in the practice's sub-account.
- GoHighLevel does not replace a dental practice-management system like Dentrix. It's the patient-communication and recall layer that runs alongside clinical charting, imaging and insurance billing, not a substitute for them.
- Hygiene recall works best tied to each patient's actual recall interval and last-visit date via a custom field, not a blanket reminder blast sent to the full patient list on the same date every year.
- Multi-touch reminder sequences (booking confirmation, 24-hour reminder, same-day reminder) reduce no-shows more reliably than a single reminder, since different patients miss different touchpoints for different reasons.
A dental practice’s production depends on three things happening reliably: patients showing up for scheduled appointments, patients accepting the treatment plans their dentist recommends, and lapsed patients coming back for recall instead of establishing care elsewhere. Two 2026 industry benchmark reports, one from Planet DDS and one from Henry Schein One, put real numbers on how much separates an average practice from a well-run one on these three points. Much of each gap comes down to whether somebody (or something) follows up at the moment that matters. GoHighLevel’s role in a dental practice is handling that follow-up automatically.
Where the revenue actually leaks, in numbers
Dental industry benchmarking has historically leaned on stats that don’t hold up well under scrutiny. A frequently cited “38% of dental calls go unanswered” figure traces back to unsourced vendor blog posts with no named methodology, and older no-show statistics from the early 2010s still circulate as if they describe today’s practices. Two reports published in 2026 are worth building on instead, because both name their sample and methodology.
Henry Schein One’s 2026 Catalyst Index, the fifth edition of its annual benchmark, analyzes performance across tens of thousands of DSOs, multi-location organizations and private practices. It found a wide gap between average and top performers on case acceptance:
A practice presenting $500,000 in diagnosed treatment a year converts $225,000 of it at the 45% industry-average acceptance rate and $375,000 at the 75% top-decile rate. That’s a $150,000/year swing from the same diagnosed treatment, with no change to clinical volume. It’s an illustrative calculation, not a promise any specific practice will close that gap. The report ties most of the spread to clinical consistency, which automation doesn’t touch directly. What automation does touch is the declined or unscheduled plan that nobody follows up on, and Henry Schein One names visibility into declined treatment as one of the factors separating top performers.
The same Catalyst Index release reports patient retention moving the wrong way, even as scheduling efficiency improved:
Illustrative arithmetic on those averages: a practice with 1,000 active patients keeps 720 at a 72% retention rate and 640 at 64%. Those 80 lost patients are a recall-and-reactivation problem, the specific gap hygiene recall and lapsed-patient reactivation workflows are built to close.
Planet DDS’s March 2026 Dental Industry Outlook, drawn from an analysis of more than 15,000 practices on its Denticon platform, measured the same underlying behavior from a different angle:
Planet DDS ties both shifts to practices moving away from fragmented patient data and legacy tools, and to “proactive communication and scheduling systems that make it easier for patients to follow through.” That’s the direct case for automated reminders and recall: the practices moving these two numbers changed how they follow up.
The dental patient lifecycle
A GoHighLevel build for a dental practice is a set of automations attached to five recurring stages:
- Inquiry to new-patient exam. A web form, call or referral gets a fast automated response and the exam gets booked before the lead cools off, using a new-patient intake form that captures insurance and contact details up front.
- Exam to treatment plan presented. A diagnosed plan that isn’t scheduled on the spot gets flagged and enters a follow-up sequence instead of silently falling off the schedule.
- Treatment accepted to active treatment. Multi-visit treatment plans get per-visit reminders, since a missed visit mid-treatment is a different problem than a missed first visit.
- Treatment complete to hygiene recall. The patient moves onto a routine 3-, 4- or 6-month recall cadence with reminders timed to their actual interval.
- Lapsed to reactivation. A patient who passes their recall due date without booking enters a reactivation sequence with a specific reason to come back.
Core automations worth building first
No-show and cancellation recovery
Trigger: a patient is marked as a no-show or cancels with little notice.
What runs: a same-day message acknowledging the miss and offering the next available slot, with a staff callback task created automatically if there's no response within a set window.
Treatment-plan follow-up
Trigger: a treatment plan is presented but not scheduled within a set window (commonly around a week), tracked with a custom field on the contact record.
What runs: the patient is flagged in the pipeline, sent a follow-up message covering financing or insurance-benefit information, and a staff task is created for personal outreach if the plan is still unscheduled.
Hygiene recall
Trigger: a patient approaches their recommended recall interval, calculated from a last-visit-date custom field.
What runs: reminders scheduled against that specific interval, a booking link sent as the due date approaches, and escalation to a call task if the patient doesn't self-book.
Lapsed patient reactivation
Trigger: no visit within a defined inactivity window past a patient's recall due date.
What runs: a multi-touch sequence over several weeks (text, email, a call task) with a specific, time-bound reason to return, removed from the sequence automatically once the patient rebooks.
Review-request sequence
Trigger: a completed appointment is marked in the calendar.
What runs: a text or email review request sent a day or two later, applied consistently to every completed visit rather than filtered to visits staff believe went especially well.
Missed-call text-back
Trigger: an inbound call goes unanswered.
What runs: an immediate text acknowledging the missed call and inviting the caller to describe what they need, so the inquiry doesn't just move to the next practice's number.
Insurance verification reminders and pre-appointment prep
A no-show recovery workflow catches a patient who doesn’t show up; a separate, earlier automation can reduce how often a patient walks in unprepared in the first place. A pre-appointment sequence triggered a few days before a scheduled visit can confirm insurance is on file, remind the patient to bring updated coverage information for a new plan year, and flag incomplete intake paperwork. That cuts the front-desk delays and last-minute rescheduling caused by something administrative not being ready when the patient arrives.
This sits alongside the practice’s insurance eligibility verification process, which stays in the practice-management system where claims and coverage data live. GoHighLevel’s role here is the communication layer: prompting the patient to have what’s needed ready, and creating a front-desk task if a required field (insurance card image, updated ID, consent form) is still missing close to the appointment date, so the gap doesn’t surface when the patient is already in the chair.
Do multi-location and DSO practices need a different setup than a solo practice?
Yes, mechanically. A single-location practice runs its pipeline stages, calendars and workflows inside one GoHighLevel location. A multi-location group or DSO needs either separate sub-accounts per location with a shared snapshot (a reusable configuration template, per HighLevel’s own Snapshots documentation) deployed to each one, or a more centralized structure depending on how much each location’s process actually differs. The five-stage lifecycle described above holds at any scale. The account architecture underneath it needs more design work as locations grow: how many sub-accounts, how snapshots get updated and redeployed when the workflow logic changes, and how leadership reports across locations without treating each one as a fully separate system. That decision is materially bigger for a five-location DSO than for a single practice, and it’s worth scoping before the first location goes live rather than retrofitting after four more locations have already diverged from it.
How does patient data actually get from Dentrix or Eaglesoft into GoHighLevel?
Don’t assume a native, pre-built integration exists between GoHighLevel and the major dental practice-management systems (Dentrix, Eaglesoft, Open Dental). Check the HighLevel App Marketplace and your PMS vendor’s integration list for your exact system before scoping, so the gap doesn’t surface mid-build. In practice, practices bridge the two systems one of three ways. The most common is a middleware connector (Zapier, Make, or a purpose-built dental-data sync tool) that watches for specific events in the PMS (an appointment booked, a status changed to completed, a new patient created) and pushes the relevant fields into GoHighLevel as a contact update or pipeline-stage change. The second is a one-way scheduled export, where a report or data extract runs on a recurring basis (nightly is typical) and updates GoHighLevel in a batch rather than in real time; this is simpler to set up but means same-day changes in the PMS don’t reflect in GoHighLevel until the next sync. The third, used by a minority of larger practices with development resources, is a custom API integration built directly against GoHighLevel’s API and whatever integration surface the PMS vendor exposes, which gives the tightest real-time sync but costs meaningfully more to build and maintain.
Whichever path a practice takes, the field that has to sync reliably above all others is last-visit date, since it’s what hygiene-recall timing is calculated from. A recall workflow built on a custom field that only updates during a nightly batch sync, rather than in real time, will occasionally send a recall reminder to a patient who was just seen the day before. Test that field’s sync behavior specifically, since confirming the integration “works” in general won’t catch this. The extra hour is worth it before recall automation goes live to the full patient list.
How do family and household accounts work?
Dental scheduling routinely involves multiple patients, often children, booked and paid for under one parent or guardian’s contact information, which doesn’t map cleanly onto a CRM built around one contact per record. GoHighLevel handles this by keeping the guardian as the primary contact (the one who receives billing and account-level communication) while each family member who’s an actual patient gets their own contact record for recall and treatment tracking, linked back to the guardian through a custom field or tag rather than a formal household object, since GoHighLevel doesn’t have a native household/family record type the way some dental-specific PMS platforms do.
The practical effect on workflow design: a hygiene-recall automation keyed only to the guardian’s contact record will miss the fact that three different children on that account are each due for recall at different times, since their last-visit dates diverge from day one. Building recall and reminder workflows against the individual patient record, even when appointment confirmations and billing messages go to the guardian’s phone number, keeps each child’s recall cadence accurate instead of collapsing a family of four patients into a single reminder timed off whichever child was seen most recently. This distinction is easy to skip during initial setup because it doesn’t show up as a problem until the second or third divergent recall date, well after the workflow’s already live.
What GoHighLevel actually costs
GoHighLevel’s platform pricing is a fixed structure, separate from any implementation or setup cost:
Implementation (pipeline structure, HIPAA configuration and the workflow builds above) is a separate, one-time cost from the monthly subscription. See the GoHighLevel implementation cost guide for how that’s scoped and priced.
HIPAA: not compliant by default
HighLevel’s own help article says accounts are not HIPAA compliant by default, and there is no government HIPAA certification for software, whatever some marketing implies. To route real patient information through GoHighLevel, a practice (or the agency running its account) needs:
- The HIPAA add-on, $297/month billed to the agency account. It can’t be cancelled, refunded or downgraded once enabled.
- A signed Business Associate Agreement (BAA), signed inside HighLevel under Settings, then Compliance
- The HIPAA toggle switched on in Advanced Settings for the practice’s sub-account. Signing the BAA activates the package at the agency level only, and each sub-account that stores patient data has to be turned on by hand.
- A clear internal map of which workflows actually touch protected health information (PHI) and which are marketing-only
The full setup sequence and cost math are in our answer to is GoHighLevel HIPAA compliant, and other clinic types are covered in GoHighLevel for medical clinics. If an agency builds or runs the account for the practice, the agency handles patient data too and needs its own BAA with the practice.
Not every message a dental practice sends is automatically a HIPAA communication. A generic review request or a holiday-hours announcement typically isn’t, while anything referencing a specific patient’s diagnosis, procedure or treatment plan typically is. Whether a specific message counts as PHI is fact-specific; confirm your practice’s classification with a healthcare attorney before going live.
TCPA consent sits alongside HIPAA, not underneath it
HIPAA governs whether a message contains protected health information; the Telephone Consumer Protection Act (TCPA) separately governs whether a practice has the right to text a patient’s phone number using automated systems at all, regardless of what the message says. The two frameworks apply independently, which means a practice can satisfy one and still violate the other. A patient consenting to appointment-reminder texts on an intake form hasn’t automatically consented to receive texts referencing a specific treatment plan or diagnosis; if the practice plans to text at that level of detail, the consent language on the intake form needs to say so specifically. A single generic “we may contact you” checkbox won’t cover every category of message the practice might eventually send.
In practice, this means the intake and consent workflow deserves the same deliberate setup as the HIPAA add-on and BAA: mapping out, in writing, exactly which message categories the practice sends (appointment logistics, recall reminders, treatment-specific follow-up, marketing/promotional content) and confirming the consent language captured at intake actually covers each category before a workflow using it goes live. The FCC’s rule at 47 CFR 64.1200 does exempt some healthcare messages from the consent requirement, but only under tight limits (free to the patient, an immediate opt-out, and no more than one message a day and three a week), so it’s no substitute for clean consent records. This is a compliance design question a healthcare attorney should review directly; the mechanics above describe what needs deciding.
Texting from a local business number also requires A2P 10DLC registration with the carriers. HighLevel lists a one-time brand fee of $22.50 for Sole Proprietor and Low Volume Standard brands plus a monthly campaign fee, and the A2P 10DLC fee calculator adds those up for your brand type.
What it doesn’t replace
GoHighLevel is not a competitor to a dental practice-management system. Platforms like Dentrix remain the system of record for clinical charting, odontogram and perio documentation, insurance eligibility and claims processing, and imaging. None of that moves into GoHighLevel. Dedicated dental communication tools like Weave (built around integrated VoIP phone hardware) and Solutionreach (built around a large recall-template and practice-management-integration library) compete more directly with GoHighLevel’s role, each with a longer specific track record in dental than GoHighLevel has.
What should change: fewer unattended no-shows once multi-touch reminders replace a single reminder or none, more lapsed patients returning once a structured reactivation sequence replaces ad hoc front-desk follow-up, and more reviews once requests go out automatically after every completed visit. These are expected directions, not measured results or a guarantee. Your own baseline no-show rate, case-acceptance rate and patient volume determine the actual size of the return. The Henry Schein One and Planet DDS figures above are industry benchmarks to measure your own numbers against.
Common setup mistakes that undercut the automation
A handful of avoidable mistakes show up repeatedly in dental GoHighLevel builds, and each one caps how much of the case-acceptance and retention gap above the automation can close:
- Blanket recall reminders instead of interval-specific ones. Sending every patient a recall reminder on the same calendar date, rather than timing each reminder off that patient’s own last-visit date and recall interval, produces a wave of reminders that don’t match when patients are actually due. Some arrive too early to be relevant, others too late to matter.
- No staff task created when automation can’t close the loop. A treatment-plan follow-up sequence that sends messages but never escalates to a human task when the patient doesn’t respond leaves the practice where it started: a plan sitting unscheduled, just with an extra text sent.
- HIPAA add-on enabled after workflows already reference patient details. Building and testing treatment-specific messaging before the BAA is signed and the HIPAA add-on is active creates a compliance gap during the testing phase itself as well as after launch.
- Review requests filtered by staff judgment instead of sent consistently. Only requesting reviews after visits staff subjectively felt went well introduces selection bias into the review base and, more practically, means most completed visits never generate a request at all.
- No named owner for the workflows after launch. A recall or reactivation sequence built once and never revisited as the practice’s actual patient volume, staffing, or scheduling changes will drift out of sync with how the practice actually runs, the same failure mode automation in any industry runs into when nobody owns maintaining it.
What a realistic case-acceptance improvement is worth, illustrated at two practice sizes
The $150,000/year swing calculated earlier assumes a $500,000-diagnosed-treatment practice moving the full 30 points from the industry average to the top-decile rate. That’s a useful illustration of scale, but most practices shouldn’t expect to hit it through automation alone, since the Henry Schein One report ties most of that spread to clinical consistency. A more conservative, illustrative way to think about it: if treatment-plan follow-up and recall automation closes even a fraction of the follow-up-driven share of that gap, say a 5-point improvement in case acceptance, a practice diagnosing $300,000 a year in treatment sees roughly $15,000 in additional accepted treatment annually from that portion alone. A larger practice diagnosing $1,000,000 a year sees roughly $50,000 from the same 5-point shift. These are illustrative calculations built on the Henry Schein One benchmark, not a projection for any specific practice. Actual results depend on a practice’s current follow-up discipline, patient mix, and how much of its existing gap is presentation-driven versus follow-up-driven.
Rolling it out
A realistic build runs in four phases:
- Setup and HIPAA configuration. Account setup, HIPAA add-on, signed BAA and the sub-account HIPAA toggle, pipeline stages matched to the five-stage lifecycle above, calendars split by exam/hygiene/restorative appointment type.
- Reminders and no-show recovery. The reminder sequence and no-show/cancellation recovery workflow, tested on a subset of appointments before full rollout.
- Treatment-plan and recall automation. Treatment-plan follow-up, hygiene recall and lapsed-patient reactivation, launched to the full active patient base.
- Reviews, missed calls and refinement. Review requests, missed-call text-back, and a review of early no-show and case-acceptance data to refine messaging and train front-desk staff on exceptions.
Is it a good fit for your practice?
It’s a strong fit for a general or family practice with a recurring hygiene cadence and restorative treatment planning, a no-show rate that’s clearly costing production, or a meaningful base of overdue-recall patients with no structured system chasing them back. It’s a weaker fit for a single-visit specialty-referral practice with minimal recurring recall, or a practice whose top priority is integrated VoIP phone hardware specifically, where a purpose-built tool like Weave is the more direct match.
If you’re scoping a build for your own practice, the GoHighLevel implementation services page covers what a properly structured, HIPAA-configured setup includes, and the GoHighLevel implementation cost guide breaks down what that setup work typically costs separate from the platform’s own monthly pricing, by scope and location count.
To have recall, no-show and new-patient workflows built for you, see GoHighLevel setup for dental practices.
Sources
- Henry Schein One, 2026 Catalyst Index press release, May 14, 2026 (case acceptance 45% vs 75%, retention 72% to 64%). Checked October 7, 2026.
- Henry Schein One, DSO case acceptance rate (Catalyst Index findings), June 8, 2026. Checked October 7, 2026.
- Planet DDS, 2026 Dental Industry Outlook, March 11, 2026. Checked October 7, 2026.
- HighLevel, pricing page. Checked October 7, 2026.
- HighLevel Help Center, HIPAA Compliance With HighLevel, modified June 11, 2026. Checked October 7, 2026.
- HighLevel Help Center, A2P 10DLC fees, modified September 24, 2026. Checked October 7, 2026.
- 47 CFR 64.1200, TCPA consent rules and healthcare message exemption. Checked October 7, 2026.